
Neuropathic pain mechanisms explained: sensitization, ectopic firing, sodium channels, common causes, screening tools and mechanism-based care.
Topics
Depression by Age and Gender: Clinical Considerations
How depression can differ by age and gender, from reproductive transitions to late-life cognitive symptoms, screening, and safety.
Anticonvulsants Beyond Epilepsy: Uses, Mechanisms, Cautions
How anticonvulsants work, their approved uses beyond epilepsy, and key safety issues: HLA-B*1502, valproate in pregnancy, interactions and monitoring.
Urinary Tract Infections: How Treatment Has Evolved
How UTI testing, antibiotic choices, OTC relief, resistance, and warning signs shape modern urinary tract infection treatment.
Respiratory Tract Infections: Treatment and Antibiotics
How respiratory infections are treated, when antibiotics help, what eases symptoms, and which warning signs need medical care.
CME review
Postoperative Pain Management: Current Trends
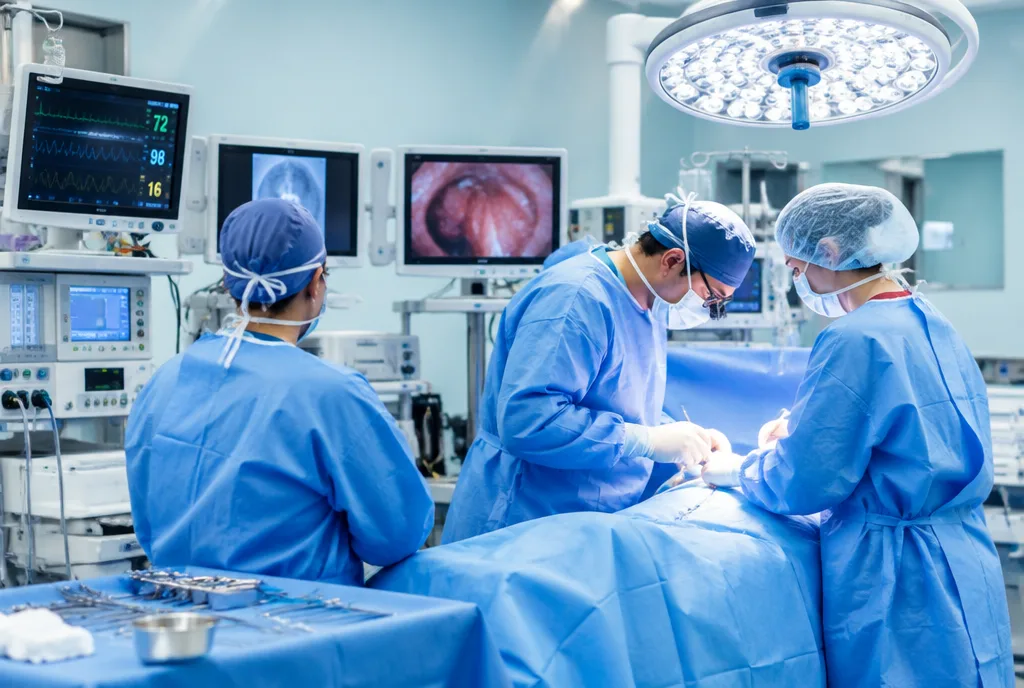
Postoperative pain management is moving away from a single-drug, pain-score-only approach. Current practice combines treatments that act through different pathways, measures pain during the activities that matter for recovery, and uses opioids selectively rather than automatically. The practical aim is not simply a lower number on a scale: it is safer breathing, movement, bowel recovery, sleep, and a plan for pain after discharge.
Postoperative pain management starts with function, not a single number
Postoperative analgesia means treatment intended to reduce pain after surgery. Pain intensity still matters, and the 0-to-10 Numeric Rating Scale (NRS) is the most commonly used validated measure: 0 means no pain and 10 means the worst imaginable pain. But a score at rest can miss the pain that limits coughing, walking, or getting out of bed.
For that reason, assessment should include pain at rest and during movement, with measurements at defined time points and attention to trends. Dynamic pain better predicts functional recovery than a resting score alone. A change of about 1 to 2 NRS points is the minimal clinically important difference; smaller changes may be statistically detectable without being meaningful to the patient.
| Assessment question | Why it changes care planning |
|---|---|
| What is the pain score at rest? | Captures baseline symptom intensity. |
| What happens with coughing or walking? | Shows whether pain is obstructing recovery tasks. |
| Is the score changing over time? | Distinguishes a trend from one isolated measurement. |
| Is function improving? | Keeps the focus on recovery, not the number alone. |
Multimodal analgesia reduces reliance on any one drug
Multimodal analgesia uses two or more analgesic agents or therapies with different mechanisms, such as acetaminophen, NSAIDs, gabapentinoids, and regional anesthesia. The combination is designed to produce pain relief through more than one pathway while reducing opioid requirements. CMS Quality Measure ID #477 describes multimodal pain management as using multiple classes of pain medications or therapies that work through different mechanisms.
In a 2025 quasi-experimental study of 60 patients, multimodal analgesia produced significantly lower VAS pain scores at 6, 12, and 24 hours after surgery than standard opioid-only care. Another 2025 study found that dexamethasone plus NSAIDs, rather than acetaminophen, produced the greatest reduction in postoperative pain and opioid use. A multimodal plan is therefore not a fixed checklist of every possible medication.
One strategy is preemptive analgesia, in which non-opioid analgesics begin before the surgical incision. This approach can reduce intraoperative opioid needs and postoperative pain intensity.
Opioid-sparing care preserves pain control while limiting exposure
Opioid-sparing analgesia adds non-opioid treatments rather than assuming opioids must carry the entire pain-control plan. A 2025 systematic review and meta-analysis of adult randomized trials found that these approaches significantly reduced postoperative pain and opioid-related adverse events without compromising pain control.
Perioperative intravenous lidocaine infusion in abdominal surgery can reduce postoperative opioid consumption by up to 85% while speeding return of bowel function. Intraoperative ketamine can reduce postoperative opioid use and pain scores, particularly for opioid-tolerant patients and people with chronic pain before surgery. Acetaminophen provides reliable relief for mild to moderate postoperative pain and has a consistent opioid-sparing effect across procedures.
Prescribing also needs to match actual use. In a Mayo Clinic survey, 92% of surgical patients received an opioid prescription at discharge, while 63% of prescribed pills went unused. Median use across procedure types was about six 5-mg oxycodone tablets, and 28% of patients said they had received too many. The 2022 CDC guideline advises the lowest effective dose for the shortest expected duration, tailored to the individual patient; it removed the former strict under-seven-day recommendation. Instead of hard MME limits, it advises caution above 50 MME per day and extra precaution above 90 MME per day. Abrupt discontinuation or rapid forced tapers are discouraged unless there are signs of life-threatening overdose, such as confusion, sedation, or slurred speech, which require urgent medical attention.
Regional anesthesia can target pain near the surgical site
Peripheral nerve blocks provide regional analgesia and can be better tolerated with fewer systemic side effects than oral pain medicines or general anesthesia alone. More than 100 million surgical procedures take place in the United States each year, and over 60% of patients receive some form of regional anesthesia or nerve block. Techniques are selected by surgical site: fascial plane blocks may be used for chest or abdominal surgery, brachial plexus blocks for arm surgery, and femoral or adductor canal blocks for lower-limb and knee surgery.
A single-injection block can reduce immediate postoperative pain, but pain may rise sharply when it wears off. This rebound pain is temporary; continuous catheter techniques can help mitigate it. Continuous peripheral nerve blockade typically lasts 48 to 72 hours and may reduce the risk of chronic postsurgical pain when used for an extended duration.
Peripheral nerve blocks also carry risks, including nerve injury, hematoma, local anesthetic systemic toxicity (LAST), allergic reactions, and infection.
ERAS makes pain control part of the whole recovery pathway
Enhanced Recovery After Surgery (ERAS) programs connect preoperative, intraoperative, and postoperative care through a collaborative team approach. Multimodal and preemptive analgesia sit alongside early mobility, early oral feeding, goal-directed fluid therapy, avoidance of prolonged fasting, and standardized prevention of postoperative nausea and vomiting.
ERAS programs that include multimodal and preemptive analgesia can support earlier mobility, earlier return of bowel function, shorter stays, and fewer readmissions. Examples of ERAS elements include a clear isotonic carbohydrate drink before surgery, patient education on incentive spirometry, and procedure-specific measures such as alvimopan before bowel surgery at UCSF.
Preventing persistent pain begins before discharge
Among approximately 40 million people who undergo surgery in the United States each year, about 1 in 10 develops chronic postsurgical pain and 1 in 100 develops severe chronic postsurgical pain that substantially impairs quality of life. Inadequate acute pain control is a major risk factor, alongside preoperative opioid use, a history of substance abuse, and high postoperative opioid consumption.
Between 35% and 57% of people with chronic postsurgical pain have a neuropathic component. Perioperative ketamine reduced chronic postsurgical pain at three and six months in a meta-analysis of 14 randomized trials. Perioperative lidocaine infusion may reduce chronic postsurgical pain at three months, particularly after breast cancer surgery. Gabapentinoids reduce acute postoperative opioid requirements but do not consistently prevent chronic postsurgical pain overall, although they may reduce its neuropathic component.
Follow-up matters for people at higher risk. Transitional Pain Service models can provide up to six months of multidisciplinary care after discharge, bringing together opioid tapering, multimodal analgesia, physiotherapy, and psychological support. Such follow-up addresses a real gap: 3% to 14% of previously opioid-naive surgical patients continue opioid use for more than three months after leaving the hospital.
Three myths that can weaken a recovery plan
Myth: More opioid pills always mean better pain control
More medication does not automatically improve outcomes. In the Mayo Clinic survey, 90% of surgical patients were satisfied with pain control even though 63% of prescribed opioid pills went unused, and fewer than 10% disposed of leftover opioids appropriately. Shared decision-making and preoperative education can reduce excess opioid burden and leftover medication.
Myth: A low pain score at rest proves recovery is on track
Resting pain is only one measurement. Pain during coughing and ambulation may reveal a barrier to recovery that a resting score does not show.
Myth: A nerve block ends the need for a plan
Single-injection blocks are effective for immediate pain reduction, but rebound pain can occur as the block resolves. A plan that anticipates that transition is different from assuming the block covers the entire recovery period.
Frequently Asked Questions
What are the main types of postoperative pain?
Postoperative pain is usually described by timing and character: acute pain after surgery, rebound pain when a single-injection nerve block wears off, and chronic postsurgical pain that persists for months. Chronic postsurgical pain includes a neuropathic component in 35% to 57% of affected patients.
What does postoperative analgesia mean?
Postoperative analgesia means pain treatment after surgery. It can include medications, regional anesthesia, and recovery-pathway measures that support movement, breathing, bowel function, and sleep.
Can a postoperative pain management PDF replace a clinical plan?
No. A document can support discussion, but postoperative care must be tailored to the procedure and the individual. Pain that is severe or worsening, or confusion, sedation, or slurred speech, needs clinical assessment rather than self-management from a document.
What should a postoperative pain management guideline cover?
Useful guidelines answer practical questions: whether pain is assessed at rest and with movement, how non-opioid and regional options are considered, and how opioid prescribing and follow-up are planned. Older guideline documents predate the 2022 CDC opioid guideline, which changed several prescribing recommendations.
What do Clinical practice guidelines for postoperative pain management in adults (2024 Edition) emphasize?
The 2024 Chinese clinical practice guidelines include 33 recommendations across 17 clinical questions and recommend continuous nerve blocks or multimodal analgesia for patients at high risk of rebound pain. Individual plans still require clinician judgment.
Information, not a course credit
The reviews on CME-CE are independent summaries for self-study. They are not accredited activities and do not replace clinical guidelines or your own judgement.